Reportable medical events at Military Health System facilities, first quarter, 2026

Image of MSMR 20268  Article 5 Photo. In the first quarter of 2026, the most frequently reported gastrointestinal illnesses among U.S. active component service members were cryptosporidiosis, norovirus, and campylobacteriosis.

Reportable Medical Events (RMEs) are documented in the Disease Reporting System internet (DRSi) by health care providers and public health officials throughout the Military Health System (MHS) for monitoring, controlling, and preventing the occurrence and spread of diseases of public health interest or readiness importance. These reports are reviewed by a team of validators from Defense Centers for Public Health (DCPH). The DRSi collects reports on over 70 different RMEs, including infectious and non-infectious conditions, outbreak reports, sexually transmitted infection (STI) risk surveys, and tuberculosis contact investigation reports. A complete list of RMEs is available in the 2022 Armed Forces Reportable Medical Events Guidelines and Case Definitions.1 Data reported in these graphs and table are considered provisional and do not represent conclusive evidence until case reports are fully validated.
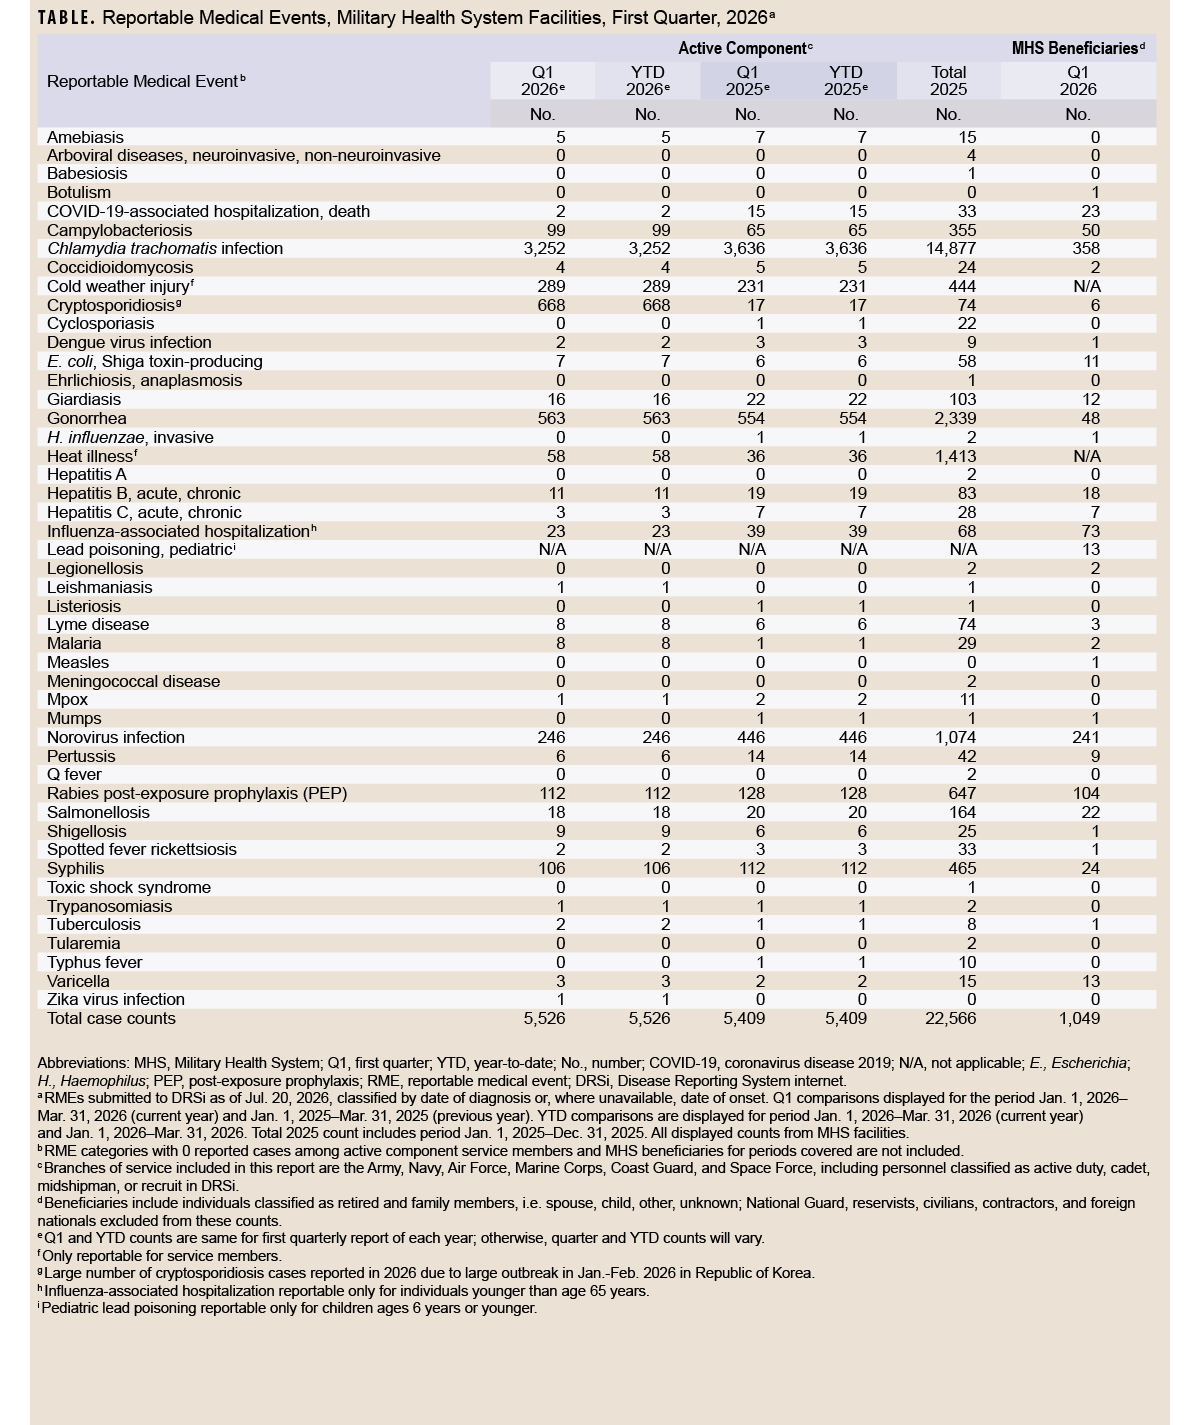
Click on the table to access and open a Section 508-compliant PDF version

Total active component cases reported per week are displayed for the 5 most frequently reported RMEs for the prior year, or preceding 52 weeks. Each quarter, the graph is updated and presented with the quarter’s (Q1, 2026) 5 most frequently reported RMEs, which may differ from those of previous quarters.
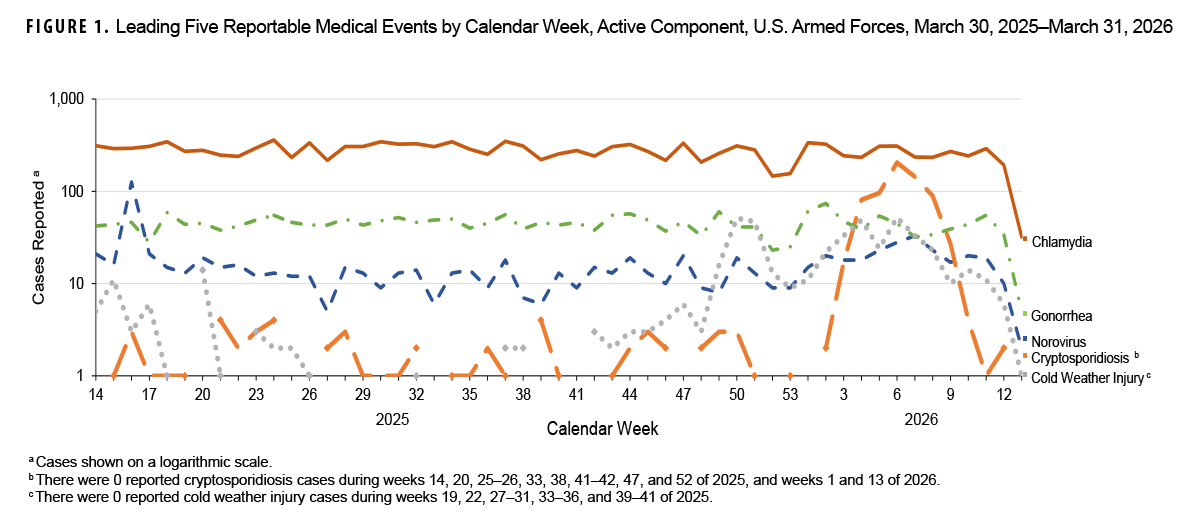
FIGURE 1. Leading Five Reportable Medical Events by Calendar Week, Active Component, U.S. Armed Forces, March 30, 2025–March 31, 2026 This multi-line trend graph plotted on a logarithmic vertical scale tracks weekly case counts for the five leading Reportable Medical Events (RMEs) among active component service members across calendar weeks 14 of 2025 through 13 of 2026. The conditions shown are Chlamydia, Gonorrhea, Norovirus, Cryptosporidiosis, and Cold Weather Injury. Chlamydia remained the most frequently reported event throughout the entire 52-week period, maintaining a steady weekly range of approximately 250 to 350 cases. Gonorrhea was consistently second, averaging 30 to 50 cases weekly. Norovirus and Cryptosporidiosis experienced major seasonal spikes during early 2026 (weeks 1 through 9), with Cryptosporidiosis jumping from near zero to over 100 cases per week due to an outbreak in the Republic of Korea. Cold weather injuries were zero or near zero during summer weeks before rising to between 10 and 50 weekly cases during late 2025 and early 2026 (weeks 47 of 2025 through 10 of 2026).

DRSi requires the reporting of numerous gastrointestinal (GI) illnesses.1 In Q1 2026, the most frequently reported GI illnesses among U.S. active component service members were cryptosporidiosis, norovirus, and campylobacteriosis. An outbreak of cryptosporidiosis occurred in the Republic of Korea (ROK), with most cases reported in January and February 2026, which contributed to a much larger number of reports of cryptosporidiosis in Q1 2026 compared to the entire calendar year of 2025. The number of reports for norovirus in DRSi were lower in January and March 2026 than in their respective months in 2025, while the number of norovirus reports in February 2026 was slightly higher than February 2025. Additionally, campylobacteriosis reports in DRSi during the months of Q1 2026 remained similar to the number of reports seen in the months of Q1 2025.
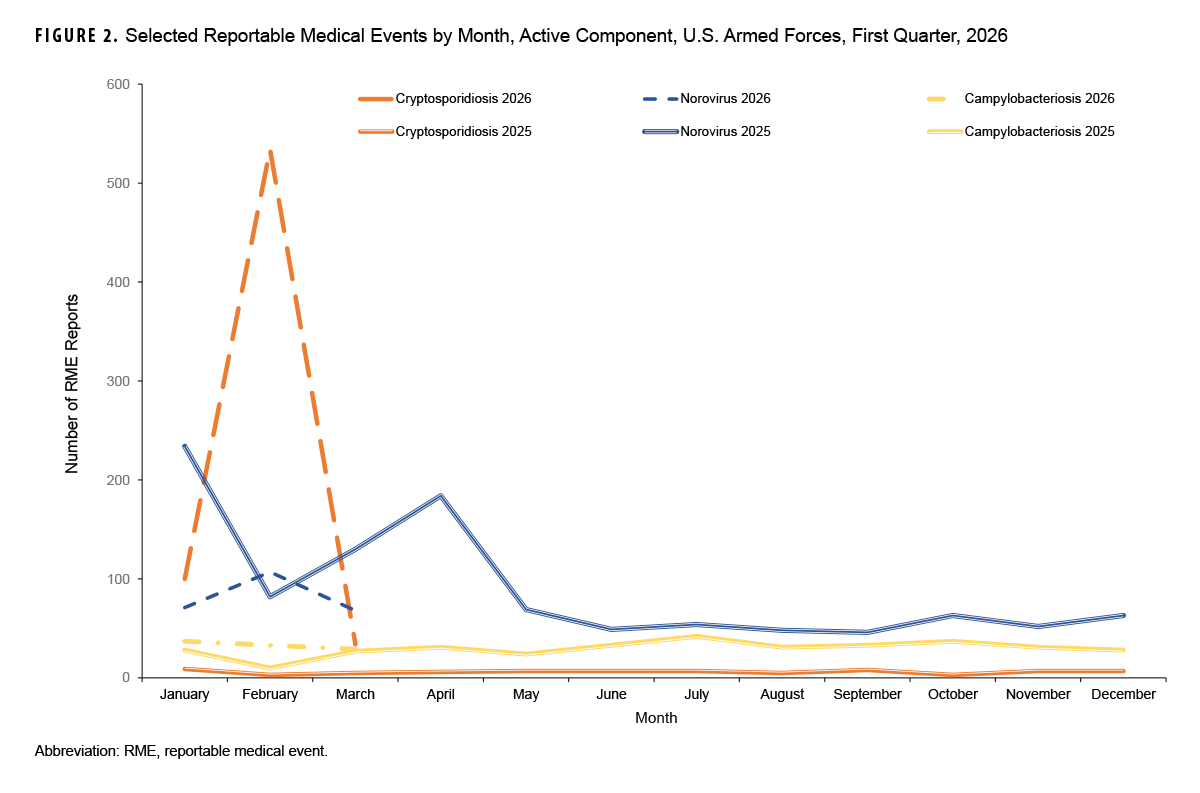
FIGURE 2. Selected Reportable Medical Events by Month, Active Component, U.S. Armed Forces, First Quarter, 2026 This multi-line comparison graph compares monthly case totals for three reportable gastrointestinal conditions (Cryptosporidiosis, Norovirus, and Campylobacteriosis) during the first quarter of 2026 (January–March) against baseline monthly data for the entire 2025 calendar year. Cryptosporidiosis experienced a large outbreak in early 2026, surging to 99 cases in January, peaking at 534 cases in February, and dropping to 35 cases in March 2026 (totaling 668 cases in Q1 2026, compared to just 74 cases across all twelve months of 2025). Norovirus counts in Q1 2026 totaled 246 cases (74 in January, 106 in February, and 66 in March), reflecting lower counts than 2025 in January (234 cases) and March (273 cases), but a higher count in February 2026 compared to February 2025 (88 cases). Campylobacteriosis remained low and steady, recording 27 cases in January, 37 in February, and 35 in March 2026 (99 total in Q1 2026), closely aligning with counts observed in Q1 2025.

DCPH-A developed the Communicable Disease Toolkit to provide guidance for reporting RME cases and outbreaks to DRSi.2 Tools such as investigation worksheets and case definition flowcharts are available in the Communicable Disease Toolkit for all RMEs, including reportable GI illnesses.

For questions about this report, please contact the Disease Epidemiology Branch at the Defense Centers for Public Health–Aberdeen. Email: dha.apg.pub-health-a.mbx.disease-epidemiologyprogram13@health.mil

References

  1. Armed Forces Health Surveillance Division. Armed Forces Reportable Medical Events Guidelines and Case Definitions. Defense Health Agency, U.S. Dept. of War. 2022. Accessed Feb. 28, 2024. https://health.mil/reference-center/publications/2022/11/01/armed-forces-reportable-medical-events-guidelines 
  2. Defense Health Agency–Public Health. Communicable Disease Toolkit. Health.mil. U.S. Dept. of War. Updated Apr. 14, 2025. Accessed Jul. 28, 2026. https://ph.health.mil/topics/healthsurv/de/Pages/cdt.aspx

Authors’ Affiliation

Defense Health Agency, Disease Epidemiology Branch, Defense Centers for Public Health–Aberdeen

You also may be interested in...

Topic
Oct. 27, 2026

Medical Surveillance Monthly Report

The Medical Surveillance Monthly Report, a peer-reviewed journal launched in 1995, is the Armed Forces Health Surveillance Division's flagship publication. The MSMR provides monthly evidence-based estimates of the incidence, distribution, impact, and trends of health-related conditions among service members.

Report
Oct. 1, 2026

MSMR Vol. 33 No. 10 - October 2026

.PDF | 1.74 MB

The October 2026 MSMR presents two full reports including a case study, in addition to one brief report and a Surveillance Snapshot. The issue features a study of flea-borne typhus fever in the U.S. military; followed by a case report of a delayed onset Plasmodium vivax malaria infection after exposure near the Demilitarized Zone (DMZ) in the Republic ...

Article
Oct. 1, 2026

Case report: Delayed onset Plasmodium vivax malaria following exposure near the demilitarized zone in the Republic of Korea: A case illustrating the importance of localized exposure history

The Republic of Korea flag flies over the Korean Demilitarized Zone in Panmujom, South Korea.

This case report describes delayed onset P. vivax malaria in a U.S. service member whose non-specific symptom presentation prompted an extensive neurological and infectious disease evaluation before a detailed operational history revealed exposure near the demilitarized zone in the Republic of Korea.

Article
Sept. 1, 2026

Health outcomes of U.S. active component service members working in high risk occupations for blast overpressure exposure: a retrospective cohort study

A U.S. Army Soldier holds his ears as he uses a 120mm Mortar Cannon in a Mortar Carrier Stryker vehicle to fire illumination flares.

This retrospective cohort study examined incidence of initial diagnoses of traumatic brain injury, insomnia, migraine headache, depressive or anxiety disorders, noise-induced hearing injury, and essential hypertension among U.S. active component service members, stratified by those who served in occupations at high risk for blast overpressure exposure ...

Report
Sept. 1, 2026

MSMR Vol. 33 No. 9 - September 2026

.PDF | 2.51 MB

The September 2026 MSMR presents four full reports, beginning with a retrospective cohort study on health outcomes of U.S. active component service members working in high risk occupations for blast overpressure exposure; followed by an inaugural Public Health Practice feature on a standardized approach to non-infectious disease cluster investigations ...

Refine your search