Seasonal changes in circulating influenza virus strains are well known and require annual updates to influenza vaccine formulations to effectively prevent or reduce the impacts of influenza infections.1 The U.S. Food and Drug Administration’s Vaccine and Related Biological Products Advisory Committee (VRBPAC) reviews and evaluates data on the safety, effectiveness, and use of vaccines, including influenza vaccines. Seasonal influenza vaccine effectiveness (VE) estimates and epidemiological, genetic, and antigenic characteristics of circulating influenza virus data are necessary to inform influenza policy-makers on the past season’s influenza characteristics and effectiveness of vaccines, to guide policy decisions for the next season.2 The most accurate data, from a variety of populations within the U.S., are essential for developing vaccines that are antigenically well-matched to circulating viruses and effective at preventing or minimizing clinical symptoms from influenza infections.
The U.S. military required annual influenza vaccinations from the 1950s through the 2025-2026 influenza season.3 This analysis was conducted to provide military leadership with timely data on influenza VE among U.S. active component service members (ACSMs) for the 2025-2026 influenza season. This analysis and evaluation is essential due to annually evolving influenza strains and vaccines.4-12
Methods
A case test-negative design was used to estimate influenza VE against outpatient cases of influenza for the 2025-2026 season. Demographic and vaccination data from the Defense Medical Surveillance System and standardized laboratory data provided by the Defense Centers for Public Health–Portsmouth were used for this analysis.13,14 The study population included all ACSMs tested for influenza from December 1, 2025 through March 31, 2026—peak influenza activity months—who had no indications of hospitalization in the laboratory data.
Cases of influenza were defined as individuals with a positive influenza result from a rapid antigen, reverse transcription polymerase chain reaction (RT-PCR), or culture influenza assay. Test-negative controls (TNCs) were individuals with a negative influenza result from a RT-PCR or culture influenza assay. Individuals with negative rapid antigen tests were excluded from the analysis due to the high false-positivity rate of those tests.15
Influenza vaccination status was determined using CVX codes for any northern hemisphere seasonal influenza vaccine (CVX codes 15, 88, 111, 135, 140, 141, 144, 149, 150, 151, 153, 155, 158, 161, 166, 168, 171, 185, 186, 197, 205, 320, 333). Service members were excluded from analysis if they had received a southern hemisphere influenza vaccine (CVX codes 194, 200, 201, 202, 231, or 331) during the surveillance period, as the study only evaluated the Northern Hemisphere formulation. Individuals who had received an influenza vaccine at least 14 days prior to the specimen collection date were considered vaccinated; otherwise they were classified as unvaccinated.
Unadjusted odds ratios (ORs) were calculated, and a multivariate logistic regression was used to calculate adjusted ORs and 95% confidence intervals (CIs). The model was adjusted for sex, age group, prior vaccination (any influenza vaccine in previous 5 years, the most suitable timeframe for this variable based on prior evaluations), and month of diagnosis. Estimates of VE were defined as (1 - OR) multiplied by (x) 100. Analyses were conducted using SAS Enterprise Guide version 8.6.
 Results
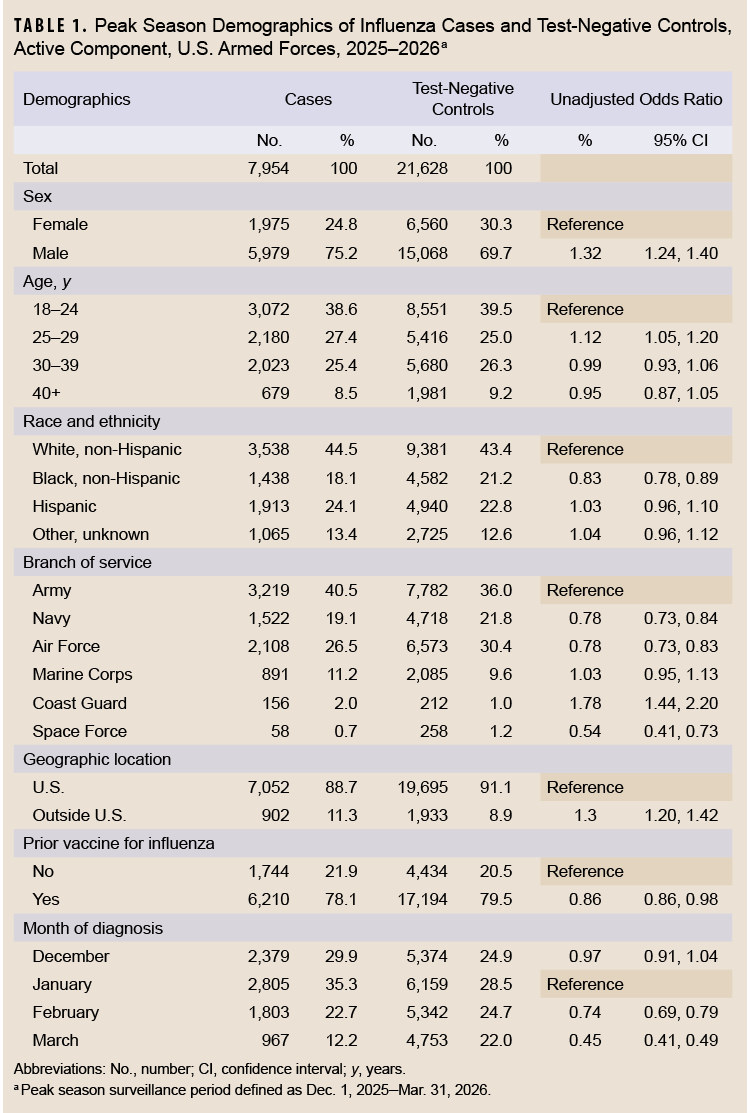
Evaluation of the data revealed 7,954 laboratory-confirmed outpatient influenza cases and 21,628 outpatient TNCs during the surveillance period. Cases were mostly influenza type A (6,221) with the remainder type B (1,706) or A and B co-infections (27). Only 14% of influenza A cases had subtype data available, of which 819 were A(H3N2) and 71 were A(H1N1)pdm09. The vaccine types administered were mostly inactivated, 79.9%, followed by cell-based (13.7%), with the remainder either ‘other’ or unknown (data not shown). Compared to TNCs, outpatient influenza cases had a statistically significantly higher odds of being male, ages 25-29 years, serving in the Coast Guard, assigned outside the U.S., and with no documented influenza vaccination in the past 5 years (Table 1).
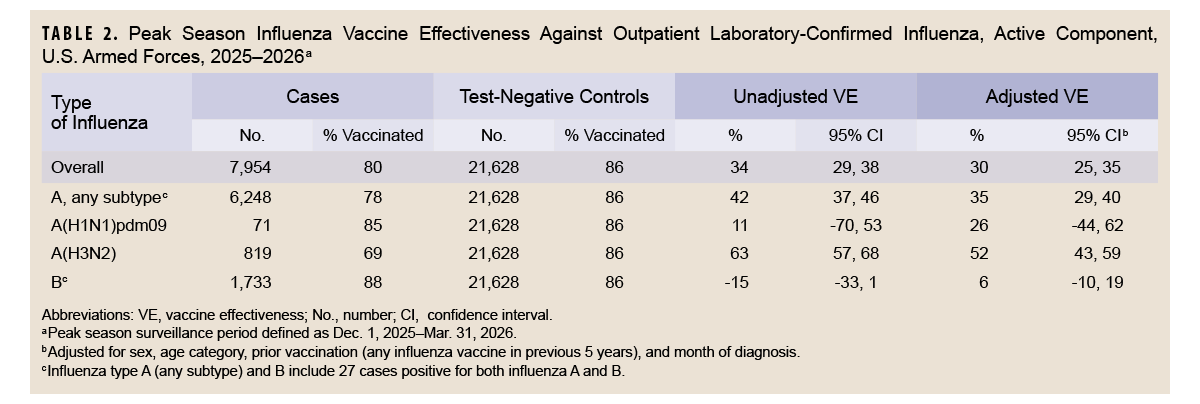
Unadjusted and adjusted VE estimates are provided in Table 2. Overall, 80% of outpatient cases were vaccinated compared to 86% of TNCs, resulting in a crude VE of 34% (95% CI 29, 38). After adjustment, the VE was 30% (95% CI 25, 35). As most cases were type A, a similar adjusted VE was found for type A overall, at 35% (95% CI 29, 40). A higher adjusted VE was seen for A(H3N2), at 52% (95% CI 43, 59). Non-significant adjusted VE estimates were found for A(H1N1)pdm09, at 26% (95% CI -44, 62), and influenza B, at 6% (95% CI -10, 19).
Discussion
This study found moderate influenza VE during the 2025-2026 influenza season against outpatient cases of influenza A among U.S. ACSMs, with the highest adjusted VE against cases of influenza A(H3N2). No statistically significant VE was seen against influenza B or A(H1N1) pdm09. These results are similar to the mid-season estimates reported by the U.S. Centers for Disease Control and Prevention (CDC) for adults ages 18-64 years in the general U.S. population for outpatient influenza A.16 The Virtual SARS-CoV-2, Influenza, and Other respiratory viruses Network (VISION) reported a 35% (95% CI 30, 39) VE against outpatient influenza A. The ACSM VE against influenza B was much lower than the VISION VE estimates (66%, 95% CI 50, 78). The difference in estimates between this study and the CDC data have been reported previously and may be affected by differences in influenza vaccine coverage (80–86% among ACSMs, 18–32% in the general U.S. population), study sample sizes, and population characteristics.7
Interpretation of these findings should be limited to the population under surveillance. This study only evaluated influenza VE against cases seeking outpatient care, and the results, therefore, do not reflect VE against more severe infections (i.e., hospitalizations) as well as less severe cases (i.e., non-medically attended). Military influenza vaccine mandates resulted in a highly vaccinated population, not only for the current season, but for past seasons as well. This may affect VE due to issues with statistical power to detect significant findings and immune responses due to repeated vaccinations.17 Vaccine data are typically only available while a member of the military is in service, so there may be misclassification of the prior vaccination variable for those who joined service less than 5 years before the season. Additionally, the reason for lack of influenza vaccination is not always documented but may include adverse reactions to prior vaccinations or temporary medical exceptions; these exceptions may introduce unmeasured confounders that were not accounted for in the analysis.
Differences in VE estimates between populations and characteristics of those populations emphasize the need for continued reporting of VE estimates among ACSMs. Seasonal changes in circulating influenza virus strains necessitate midand post-season assessments of influenza VE to inform both military and national public health leaders and policy-makers on the impacts, as well as changing needs, of vaccine formulations. These estimates provide valuable data on influenza infections among ACSMs and assess the vaccine’s ability to protect the health and readiness of service members.
References
- Trombetta CM, Kistner O, Montomoli E, Viviani S, Marchi S. Influenza viruses and vaccines: the role of vaccine effectiveness studies for evaluation of the benefits of influenza vaccines. Vaccines (Basel). 2022;10(5):714. doi:10.3390/vaccines10050714
- U.S. Food and Drug Administration. Influenza Vaccine Composition for the 2026-2027 U.S. Influenza Season. U.S. Dept. of Health and Human Services. Aug. 11, 2026. Accessed Mar. 26, 2026. https://www.fda.gov/vaccines-blood-biologics/vaccines/influenza-vaccine-composition-2026-2027-us-influenza-season
- Grabenstein JD, Pittman PR, Greenwood JT, Engler RJM. Immunization to protect the US Armed Forces: heritage, current practice, and prospects. Epidemiol Rev. 2006;28(1):3-26. doi:10.1093/epirev/mxj003
- Eick-Cost AA, Hu Z. 2023-2024 mid-season influenza vaccine effectiveness against laboratory-confirmed ambulatory influenza: U.S. active component service members. MSMR. 2024; 31(3):22. Accessed Mar. 27, 2026. https://www.health.mil/news/articles/2024/03/01/msmr-flu-vaccines-hospitalizations
- Thervil JW, DeMarcus LS, Eick-Cost A, et al. Department of Defense mid-season vaccine effectiveness estimates for the 2019-2020 influenza season. MSMR. 2021;28(6):16-19. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2021/06/01/medical-surveillance-monthly-report-volume-28-number-06
- Lynch LC, Colemand R, DeMarcus L, et al. Department of Defense midseason estimates of vaccine effectiveness for the 2018-2019 influenza season. MSMR. 2019;26(7):24-27. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2019/07/01/medical-surveillance-monthly-report-volume-26-number-7
- Coleman R, Eick-Cost AA, Hawksworth AW, et al. Department of Defense end-of-season influenza vaccine effectiveness estimates for the 2017-2018 season. MSMR. 2018;25(10):16-20. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2018/01/01/medical-surveillance-monthly-report-volume-25-number-10
- Shoubaki L, Eick-Cost AA, Hawksworth A, et al. Department of Defense midseason vaccine effectiveness estimates for the 2017-2018 influenza season. MSMR. 2018;25(6):26-28. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2018/01/01/medical-surveillance-monthly-report-volume-25-number-6
- Toure E, Eick-Cost AA, Hawksworth A, et al. Mid-season influenza vaccine effectiveness estimates for the 2016-2017 influenza season. MSMR. 2017;24(8):17-19. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2017/01/01/medical-surveillance-monthly-report-volume-24-number-8
- Cost AA, Hiser MJ, Hu Z, et al. Mid-season influenza vaccine effectiveness estimates for the 2013-2014 influenza season. MSMR. 2014;21(6):15-17. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2014/01/01/medical-surveillance-monthly-report-volume-21-number-6
- Eick-Cost AA, Hu Z, Cooper MJ, et al. Mid-season influenza vaccine effectiveness for the 2012-2013 influenza season. MSMR. 2013;20(3):15-6. Accessed Aug. 11, 2026. https://www.health.mil/reference-center/reports/2013/01/01/medical-surveillance-monthly-report-volume-20-number-3
- Eick-Cost AA, Tastad KJ, Guerrero AC, et al. Effectiveness of seasonal influenza vaccines against influenza-associated illnesses among US military personnel in 2010-11: a case-control approach. PLoS One. 2012;7(7):e41435. doi:10.1371/journal.pone.0041435
- Rubertone MV, Brundage JF. The Defense Medical Surveillance System and the Department of Defense serum repository: glimpses of the future of public health surveillance. Am J Public Health. 2002;92(12):1900-1904. doi:10.2105/ajph.92.12.1900
- Navy Medicine. Respiratory Surveillance. Department of the Navy, U.S. Dept. of War. Accessed Aug. 11, 2026. https://www.med.navy.mil/navy-medicine-research-and-development-command/r-d-commands/naval-health-research-center/core-research/operational-infectious-diseases/respiratory-surveillance
- Centers for Disease Control and Prevention. Information for Clinicians on Rapid Diagnostic Testing for Influenza. U.S. Dept. of Health and Human Services. Jan. 5, 2026. Accessed Apr. 24, 2026. https://www.cdc.gov/flu/hcp/testing-methods/rapidclin.html
- Centers for Disease Control and Prevention. Preliminary Flu Vaccine Effectiveness (VE) Data for 2025-2026. U.S. Dept. of Health and Human Services. Mar. 16, 2026. Accessed Aug. 11, 2026. https://www.cdc.gov/flu-vaccines-work/php/effectiveness-studies/2025-2026.html
- Jones-Gray E, Robinson EJ, Kucharski AJ, Fox A, Sullivan SG. Does repeated influenza vaccination attenuate effectiveness? A systematic review and meta-analysis. Lancet Respir Med. 2023;11(1):27-44. doi:10.1016/S2213-2600(22)00266-1
Authors’ Affiliation
Epidemiology and Analysis Branch, Armed Forces Health Surveillance Division, Public Health Directorate, Defense Health Agency, Silver Spring, MD: Dr. Eick-Cost, Ms. Hu